
Barriers to Early Licensure May Widen Teen Traffic Safety Disparities
Study Links Delayed Driver’s Licensing to Missed GDL Safety Training
Blog Post

Resource scarcity increases discriminatory behaviors and beliefs, psychology experiments show. Now, a first-of-its-kind LDI study in the American Economic Review shows that resource discrimination could occur in real-world health care.
Carnegie Mellon University economist Manasvini Singh and LDI Senior Fellow Atheendar Venkataramani found that as hospital beds became scarcer, racial discrimination increased, reflected in longer wait times and less provider effort for Black patients. They linked this unfair treatment to an increase in the racial mortality gap.
“When hospitals get busy, patient care suffers,” said Venkataramani, a practicing internist, about the results. “Increasing stress on the system interacts with preexisting differences in how Black patients are treated.”
The study used electronic health records on more than 107,000 admissions from 2015 through 2018 at two hospitals in a southeastern U.S. city with a substantial Black population. The data included patient demographics and medical backgrounds, clinical notes, and diagnostic and treatment information time-stamped to the second. Key variables included hospital strain, measured as hourly inpatient bed occupancy, wait times, and mortality.
In addition, the authors developed a novel index of provider effort by analyzing the free-text field describing each patient’s reason for admission. They calculated character counts, average word length, and the number of adjectives, and used machine learning to measure simple subjectivity and polarity of the text. Subjectivity measured the degree of opinion versus factual information, such as a description of pain, as opposed to a more objective pain score. Other studies have linked higher subjectivity to lower effort. Polarity measured whether text leaned positive or negative using words such as ‘improving’ or ‘worsening,’ which could indicate less careful documentation.
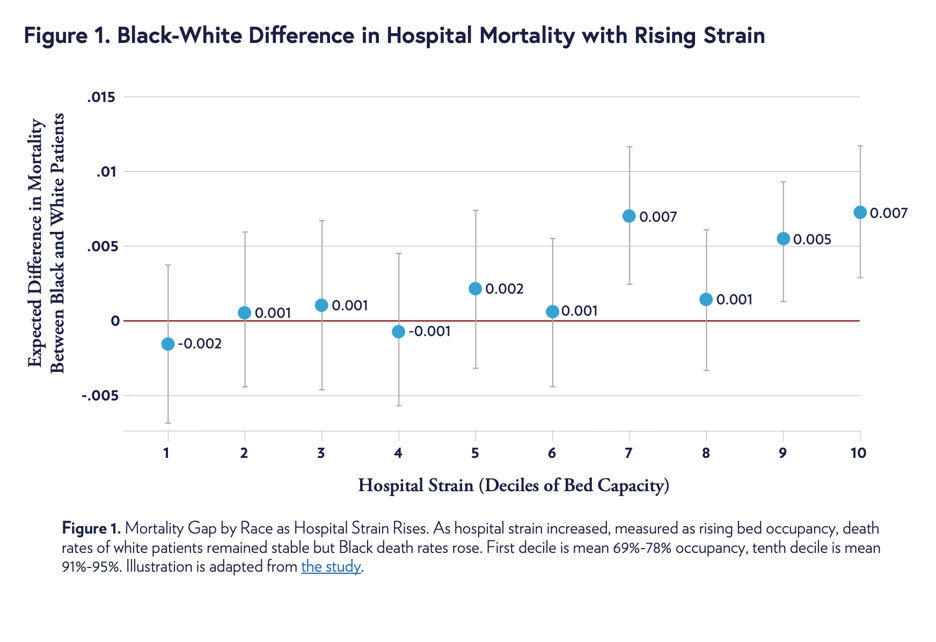
Average mortality in the sample was 1.7%. As hospital capacity rose from its lowest to its highest decile, with occupancy above 90% in the highest decile, the Black-white patient mortality gap nearly tripled (Figure 1). Across the nine lower levels of hospital strain, the mortality difference was 0.2 percentage points. At the highest level of strain, the death rate was 0.7 percentage points higher for Black patients than for white patients.
As a mechanism for the expanding racial mortality gap, the authors highlighted inequitable rationing of hospital resources, specifically beds and provider effort. Black patients waited 57 minutes longer for a bed than white patients at lower levels of hospital strain, but 78 minutes (1.3 hours) more at the highest level. The study’s innovative quantification of average provider effort via clinical-note analysis demonstrated a greater decrease in provider effort for Black relative to white patients at the highest level of strain.
The researchers tested alternative explanations related to whether the composition of Black and white patients changed with hospital strain, such as whether sicker Black patients were admitted as hospital occupancy increased. They found that characteristics of Black patients, including comorbidities, insurance status, demographics, mode of arrival, or discharge to hospice, did not differentially change with strain relative to white patients. Of note, emergency department records revealed that at all levels of strain, admitted or discharged Black patients had less urgent triage scores than white patients.
When resources are limited, rationing is inevitable. Singh and Venkataramani found significant racial discrimination in resource rationing as strain increased in an inpatient setting, with deadly consequences.
Although the data came from a single urban academic medical system and the findings’ relevance to other settings is unknown, the authors considered a general solution that could ease the negative effects of hospital strain. They said that creative approaches, including some from the COVID-19 pandemic, such as distributing patients across hospitals, might prevent any site from reaching capacity.
“Reducing the load on the system will likely have first-order effects, such as relieving stress on clinicians and staff, and, as a bonus, may also reduce racial gaps and disparities in outcomes,” Singh said.
Future research by the authors includes investigating how proposed public policies affect population health and Singh’s project, which investigates how the presence of providers on social media may help reduce medical misinformation online.
The study, “Rationing by Race,” was published in the September 2026 issue of the American Economic Review by Manasvini Singh and Atheendar Venkataramani.

Study Links Delayed Driver’s Licensing to Missed GDL Safety Training

Penn LDI Team Finds Black Immigrants, Especially Those who are Undocumented, Face Higher Rates of Uninsurance and Lower Health Care Use

Ninth Year of Program That Recruits, Mentors and Develops Junior Faculty for Health Services Research

Caregivers Must Often Go Without Food as They Accompany Child Patients

Decades of Research Show Minority Patients Less Likely to Receive Surgery, Even When Equally Indicated

Comparison to Commercial All-Payer Database Documents Wide Discrepancies